



In early September, pharmaceutical company Novartis reported that pelacarsen, a drug once expected to become a blockbuster, had failed to reduce the risk of heart disease or stroke in people with established cardiovascular disease. The result from the late-stage Lp(a)HORIZON trial surprised cardiologists because pelacarsen sharply lowers lipoprotein(a), or Lp(a), a genetically determined cholesterol-carrying particle long associated with cardiovascular risk.
Gain muscle, reduce belly fat: genetic variation is associated with a wide range of benefits
Michelle O’Donoghue, a cardiologist at Brigham and Women’s Hospital in Boston, Massachusetts, said her initial reaction was “a state of disbelief”.
Pelacarsen lowers levels of lipoprotein(a), often called Lp(a) or “Lp little a”. Like low-density lipoprotein (LDL), high levels of Lp(a) increase the risk of heart attacks and other cardiovascular problems. Unlike LDL, which is also known as bad cholesterol, Lp(a) levels are determined primarily by genetics rather than lifestyle. As a result, approximately one in five people with high Lp(a) levels cannot lower them through diet or exercise. Statins and other drugs can reduce LDL levels, but no approved medicines significantly lower Lp(a).
That is why cardiologists have been enthusiastic about pelacarsen and several other Lp(a)-lowering drugs now in late-stage clinical trials. “Lp(a) has really been a hot topic in the cardiovascular field over the last few years, in part because there’s been a lot of enthusiasm for these treatments,” says O’Donoghue, who is an investigator on one of the trials.
These treatments can reduce Lp(a) levels by more than 80%. Researchers needed to show that the reduction also improved clinical outcomes, such as reducing cardiovascular deaths, heart attacks, strokes and emergency bypass surgeries.

Rank your risk of heart disease
It is not yet clear why the Lp(a)HORIZON trial failed. Novartis’s announcement of the phase III topline results is available here. Representatives for Novartis did not respond to requests for comment.
The high-profile setback has left cardiologists questioning what they know about the relationship between Lp(a) and major cardiovascular problems, and wondering whether other Lp(a)-lowering therapies could meet a similar fate. US pharmaceutical companies Amgen and Eli Lilly are conducting large-scale clinical trials of treatments that target Lp(a) through a different approach.
“We were hoping this would be the first step into a big new field of treatment,” says Harpreet Bhatia, a cardiologist at the University of California, San Diego. He and other researchers are now waiting for more details from the Novartis trial, as well as results from other studies, to determine whether Lp(a)-lowering treatments still have a future.
Hidden cholesterol
Both Lp(a) and LDL carry cholesterol, a fatty substance produced primarily in the liver. The body needs cholesterol, but high levels can cause it to accumulate on artery walls, forming hard plaques known as atherosclerosis. These plaques can grow thick enough to block blood flow or rupture, triggering blood clots that can cause a heart attack.
Study after study has found that people with high Lp(a) levels have a greater risk of coronary artery disease, including heart attacks, heart-valve problems and heart failure, than do people with low levels.1 Over the past 30 years, genetic data have strengthened the idea that Lp(a) is not merely a marker of risk but also a causal factor.2
“Genetically, I don’t think there is any further evidence that this is a drug target,” says Borge Nordestgaard, a cardiologist at the University of Copenhagen and president of the European Atherosclerosis Society in Gothenburg, Sweden.
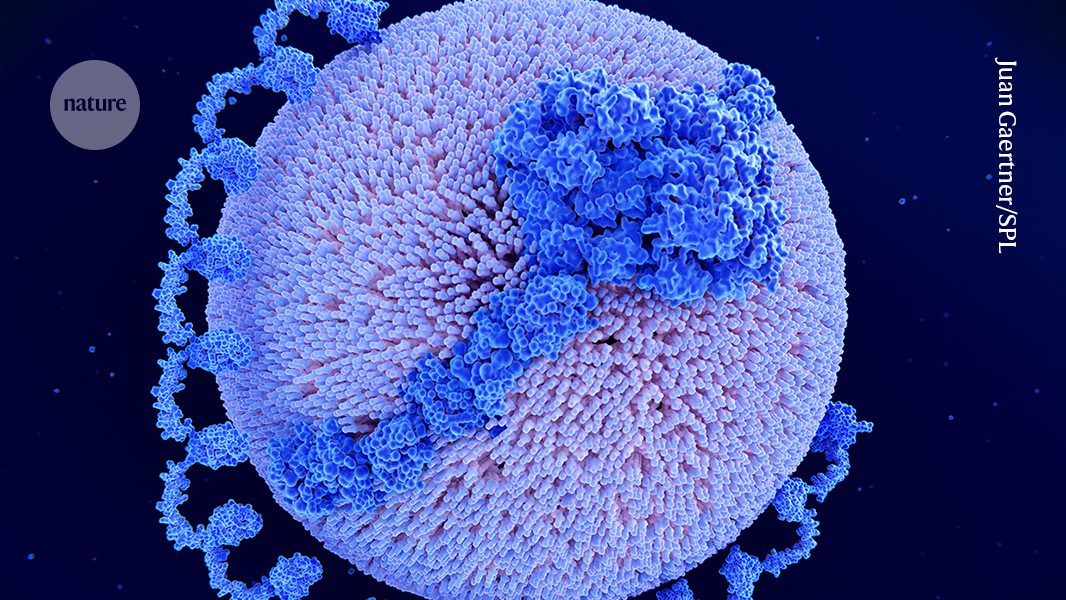
Structurally, Lp(a) is not very different from LDL. Both are essentially particles of fat surrounded by a protein called apolipoprotein B. Both are produced in the liver. The main difference is that Lp(a) has a tail made of apolipoprotein(a), which loops through a segment called a “kringle”, named after a twist in a Scandinavian pastry.
Lp(a) levels depend partly on the number of copies of a particular type of kringle encoded by the apolipoprotein(a) gene. People carry between one and more than 40 copies. The fewer copies they have, the smaller the particle and the higher their Lp(a) level. Liver cells seem to produce and secrete smaller particles more easily.

Researchers are still working to understand how structural differences affect the particle’s function and its role in cardiovascular disease. On a particle-for-particle basis, Lp(a) carries six times the risk of LDL. This could be because it deposits cholesterol on artery walls efficiently or because it promotes inflammation that contributes to plaque formation. Nordestgaard thinks the main effect could instead involve blood clotting. The particle’s tail might make it harder for the body to break down a blood clot, allowing a larger blockage to form.
Many countries recommend that adults have their Lp(a) levels tested at least once. The European Atherosclerosis Society and the Society of Cardiology first recommended testing in 2019, and American societies followed suit earlier this year. There are no approved treatments that lower Lp(a), so the standard approach for people with high levels is to reduce other cardiovascular risk factors aggressively.
High Lp(a) levels do not always lead to cardiovascular problems. Bhatia says that some older people have high Lp(a) levels but have not experienced cardiovascular events. “In some cases, plaque may not be visible on imaging tests,” he says. “It’s a big picture of risk, and Lp(a) may be just one piece of that big puzzle.”
Many unanswered questions
Source: www.nature.com







